
Aesthetic Clinic Doctor Commission, Schedules and Utilisation: How to Manage Doctors and Practitioners
WAJ Team
September 20, 2026

Aesthetic clinic doctor commission works best when it sits on top of a clear schedule, a written policy for product cost deductions and a utilisation number everyone can see. Most clinics pay doctors in one of three ways: a fixed salary, a salary plus commission, or a revenue share. The right choice depends on how many hours the doctor is in the building, whose patients they are, and how much risk each side wants to carry.
The hardest pay conversations I've seen in clinics in Dubai and Riyadh were rarely about the percentage. They were about what the percentage was calculated on. A doctor sees AED 3,000 on the invoice and expects a share of AED 3,000. The owner has already taken off filler, needles, VAT and a discount reception gave without asking. Both are right by their own maths, and both feel cheated. Most of this guide is about preventing that.
Who is allowed to do what? Start with scope
Before you design a single shift, write down who may perform which treatment. The DHA treats injectables and medical lasers as medical acts, for licensed clinics and qualified practitioners only. A beauty therapist cannot inject, however experienced she is.
That shapes the calendar directly. A toxin slot should only open when a licensed doctor is on shift, and a laser slot only when a practitioner qualified for that device is free. If your system lets reception drop an injectable into a therapist's column, fix the system before it causes a real problem.
Rules differ by emirate and country, and they change. Confirm scope of practice with the DHA, DOH or MOH and your medical director, and have a lawyer review doctor contracts.
How to schedule part-time and visiting doctors
Many Gulf clinics run on one or two full-time doctors plus a visiting dermatologist who comes in two afternoons a week. Visiting doctors bring a name and a following, and some constraints:
- Fixed days. Patients learn to book "Tuesday with Dr. Rania". Don't let a laser course take her room that day.
- Early rosters. Get the visiting doctor's dates two to three weeks ahead and open them for online booking.
- Follow-ups. If she only visits on Tuesdays, the two-week review also lands on a Tuesday. Book it before the patient leaves.
- Cover. Agree in writing who handles a complication on days she isn't there.
How to build doctor schedules around demand
Start from booking history, not from what the doctors would prefer. Pull three months of appointments and look at bookings by day and hour, split by treatment type. Most clinics see the same shape: evenings and weekends full, weekday mornings thin.
- Map demand by day and two-hour block for each treatment group: injectables, lasers, skin, consultations.
- Place licensed doctors first on the blocks with the most injectable and medical demand.
- Fill the shoulders with follow-ups, reviews and lower-demand treatments.
- Keep one flexible block per doctor per week for overflow or complications.
- Review monthly and move hours to where the bookings actually are.
Consultation slots vs treatment slots
Mix consultations and treatments with no rules and a doctor ends up with five free 15-minute consultations on a Thursday evening, the clinic's most valuable time. Give each doctor fixed consultation blocks in quieter hours, such as weekday late mornings, and protect peak evenings for treatments. Keep consultations a set length, usually 20 to 30 minutes, and decide whether a paid consultation fee comes off the treatment if the patient goes ahead. Then tell reception and put it on the website.

Aesthetic clinic doctor commission: comparing pay models
The figures below are invented examples to show how each model behaves. They are not market rates.
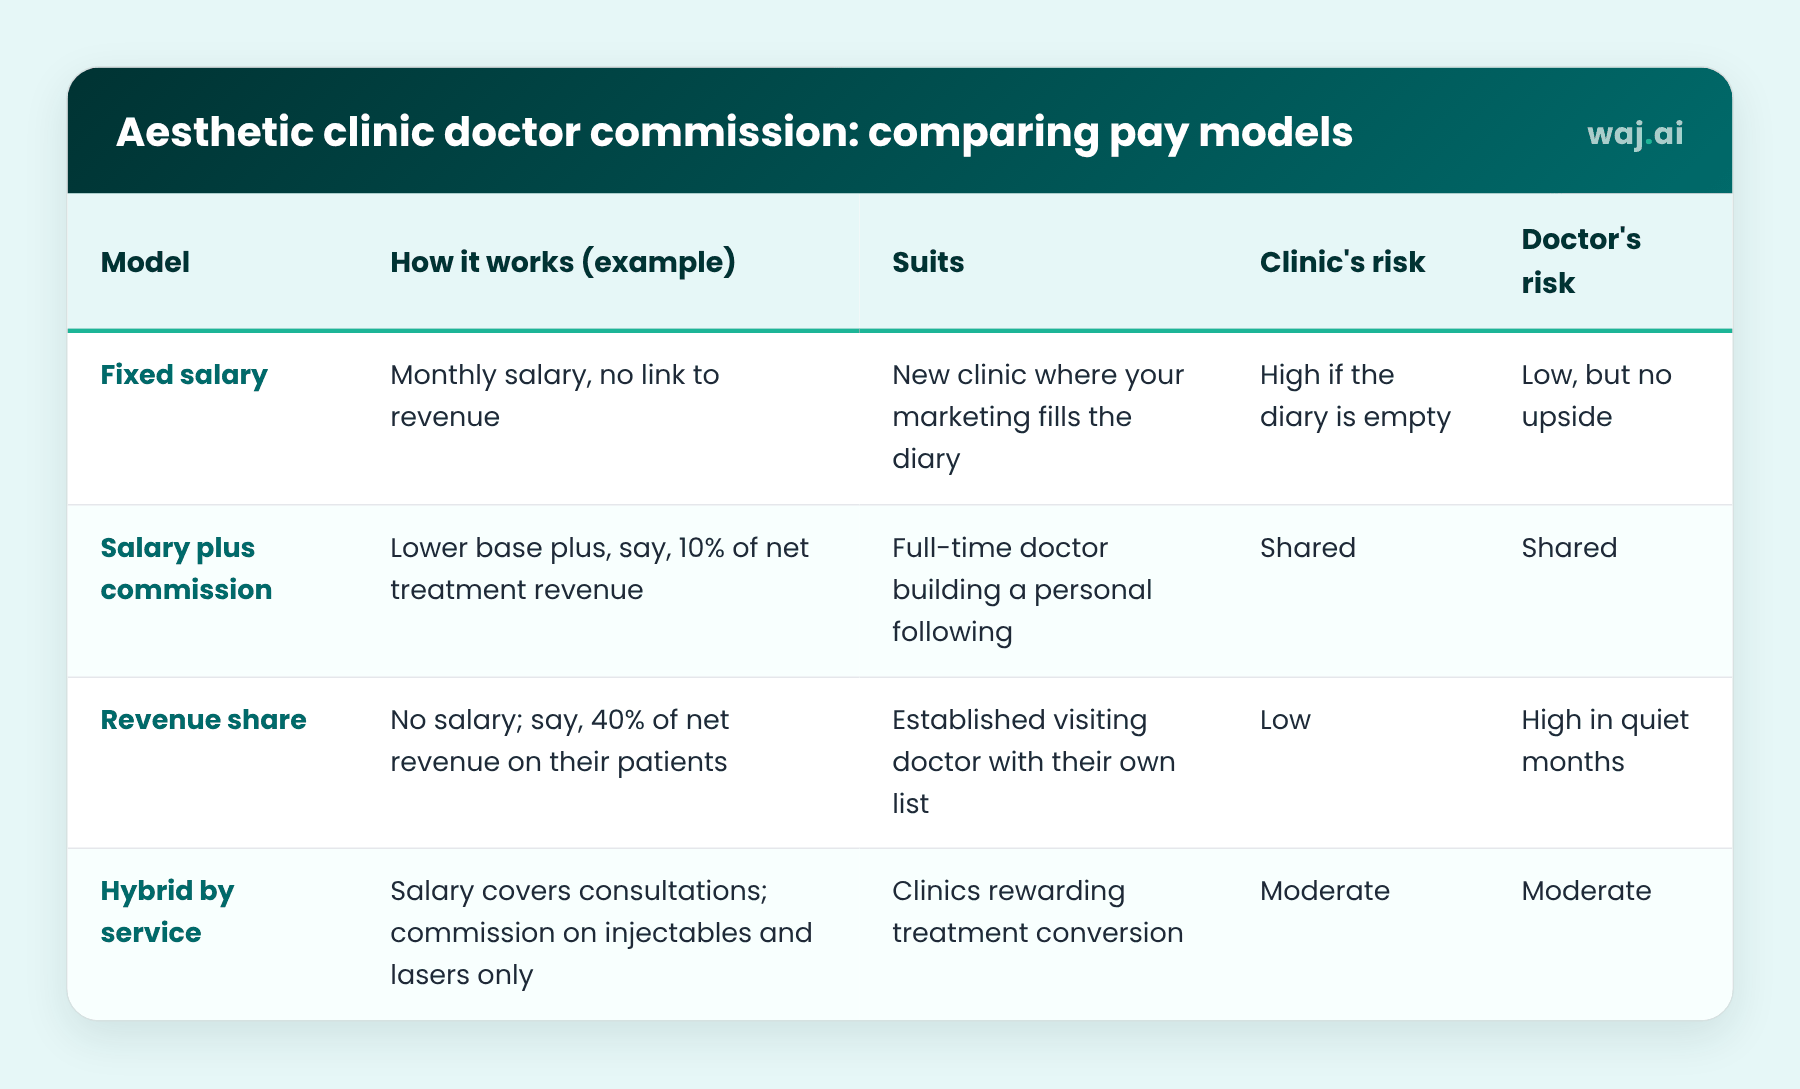
- Fixed salary
How it works (example): Monthly salary, no link to revenue
Suits: New clinic where your marketing fills the diary
Clinic's risk: High if the diary is empty
Doctor's risk: Low, but no upside - Salary plus commission
How it works (example): Lower base plus, say, 10% of net treatment revenue
Suits: Full-time doctor building a personal following
Clinic's risk: Shared
Doctor's risk: Shared - Revenue share
How it works (example): No salary; say, 40% of net revenue on their patients
Suits: Established visiting doctor with their own list
Clinic's risk: Low
Doctor's risk: High in quiet months - Hybrid by service
How it works (example): Salary covers consultations; commission on injectables and lasers only
Suits: Clinics rewarding treatment conversion
Clinic's risk: Moderate
Doctor's risk: Moderate
A worked example
A doctor's completed treatments come to AED 60,000 in a month, before VAT.
- Discounts given: AED 3,000
- Product cost (filler syringes, toxin units, consumables): AED 12,000
Net base = 60,000 − 3,000 − 12,000 = AED 45,000.
At 10% commission that's AED 4,500 on top of salary. At a 40% revenue share it's AED 18,000 with no salary. What matters is that the doctor can see every line that took 60,000 down to 45,000.
Product cost deductions: where fairness is won or lost
Product cost moves the numbers far more in an aesthetic clinic than in a hair salon. Three rules keep it calm:
- Use a standard cost per unit or syringe, agreed in writing and reviewed each quarter, rather than whatever the last supplier invoice said.
- Deduct what was actually used, as recorded in the treatment notes, not an end-of-month estimate.
- Decide who carries waste. Stock that expires because the clinic over-ordered is the clinic's cost. Agree in advance how an unnecessary second syringe is handled.
Discounts need the same clarity. One common approach: commission is calculated on the pre-discount price for clinic campaigns the doctor didn't agree to, and on the discounted price when the doctor offered the discount personally. Any rule works if it's written down.
How to track practitioner utilisation
Utilisation is the share of a practitioner's rostered hours spent with patients. Rostered for 40 hours, treating or consulting for 28, utilisation is 70%. Track it weekly per doctor, and split it into treatment vs consultation hours, peak vs off-peak, and no-show time, which looks like utilisation on paper and isn't.
Low utilisation with a waiting list is a scheduling problem. Low utilisation with no waiting list is a demand problem. Recurring patients help a lot here: a clinic with a steady base of members knows roughly how many maintenance visits are coming each month, which makes rostering easier. Our piece on the aesthetic clinic membership model explains how to set that up.

Fairness and transparency: what doctors actually ask for
In my experience, doctors ask to understand the numbers before they ask for a higher percentage. What builds trust:
- A one-page pay policy showing the base, deductions and rate, with a worked example.
- A monthly statement per doctor listing each treatment, the product deducted and the commission earned.
- Clear patient ownership rules. Is a patient who books through the clinic's Instagram the clinic's or the doctor's? This matters most under revenue share and when a doctor leaves.
- Rotation of peak hours if two doctors both want Thursday evenings.
- A fixed pay day for commission, every month, without anyone having to chase.
Where WAJ fits
WAJ takes the manual work out of this: a staff calendar where each service can be limited to the practitioners allowed to perform it, online booking, patient records with treatment notes and history, inventory for product tracking, staff commissions, and reports by practitioner that give you a starting point for utilisation. Our guide to aesthetic clinic management and automation covers the wider setup. WAJ's clinic product, Nabd, runs on the same platform, with no booking commission and no onboarding fee.
To see your own doctors' week laid out, book a free WAJ demo: waj.ai/demo.
FAQ
What is a typical aesthetic clinic doctor commission?
There's no single typical rate. It depends on whether there's also a salary, who brings the patients, and how product costs are treated. Agree the base before you agree the percentage.
Should commission be on gross or net revenue?
Most clinics use net: invoice value excluding VAT, minus agreed discounts and a standard product cost. Commission on gross injectable revenue can leave the clinic losing money on expensive products.
How should a clinic pay a visiting doctor?
Revenue share on their own patients is common for established visiting doctors, because the clinic carries little fixed cost. Put patient ownership, follow-up cover and notice periods in the contract.
Can a beauty therapist give injectables under a doctor's supervision?
The DHA treats injectables as medical acts for qualified practitioners in licensed clinics. Confirm the exact scope for your licence with your regulator.
What utilisation rate should I aim for?
Set a target from your own booking history and review it monthly. The trend, and the peak vs off-peak split, tell you more than one number.
Follow WAJ on Google
Add WAJ as a preferred source to see more of our articles in your Google Search results, marked with a "preferred" badge.